

The Pediatrics COMAT is the pediatrics subject examination in the Osteopathic Medical Achievement Test (COMAT) series, administered by the National Board of Osteopathic Medical Examiners (NBOME), and most osteopathic students sit it at the end of their pediatrics clerkship. It runs 120 items in 2.5 hours and reports a scaled score rather than a percentage, which is why practice percentages from different question sets tell you less than you'd expect.
The clinical stakes behind those items are concrete. In a tertiary pediatric hospital in Douala, Cameroon, 46 of 109 children hospitalized with coma had cerebral malaria and 29 died, a mortality rate of 26.6% (2025 BMC Pediatrics cohort study). Sick children rarely present in textbook form, and the exam is built to see whether you can find the one finding that changes the next action.
Preparation pays off most when it's organized around tasks: recognize, test, interpret, manage, then decide disposition. Blueprint weights, pacing math and a working study routine carry more value than another pass through a disease list.
What the Pediatrics COMAT Is and How the Exam Is Built
Pediatrics COMAT is a Clinical Subject examination in the COMAT series, written for osteopathic medical students on a pediatrics rotation rather than for practicing pediatricians. The series is produced by NBOME, an independent nonprofit organization that builds osteopathic medical assessments. Your college of osteopathic medicine decides how the result counts in your grade, so the exam's purpose and your school's purpose are separate things.
The format is fixed and published. Each COMAT Clinical examination consists of 120 items completed within 2.5 hours, preceded by a 5-minute tutorial (NBOME COMAT exam series). That averages 1.25 minutes per scored item, though nothing stops you from moving faster on short items to protect time for long vignettes. The tutorial is orientation rather than question time.
The series uses multiple forms built to be psychometrically equivalent in content coverage, difficulty and reliability, which matters for how you practice. Memorizing one question set teaches you that set. Working across varied items teaches you the decision pattern the exam is sampling.
COMAT versus the NBME pediatrics shelf
These are two exams from two organizations, and blending their materials costs students time. The NBME pediatrics subject examination, usually called the shelf, comes from the National Board of Medical Examiners. COMAT comes from NBOME. Different organizations, different series, different scoring.
Shelf question sets remain useful for pediatric content review. What you shouldn't assume is that their format, item style or score scale mirror what you'll meet on COMAT. Confirm the format from NBOME and confirm your school's grading policy from your program office.
| Feature | Detail | Study implication |
|---|---|---|
| Scored items | 120 | Practice in blocks that match the full item count |
| Testing time | 2.5 hours | About 1.25 minutes per scored item on average |
| Tutorial before the exam | 5 minutes | Orientation time, not part of the scored-question budget |
| Form design | Multiple forms built to be psychometrically equivalent | Practice across varied items, not one fixed set |
| Administration frequency | A college may give a subject exam up to 10 times per year | Ask your school when your sitting is scheduled |
| Grading and performance policy | Set by each college of osteopathic medicine | Confirm your school's policy with your program office |
Three numbers worth committing now: 120 items, 2.5 hours, 5 minutes of tutorial.
Blueprint Weights and Where the Questions Concentrate
The official blueprint gives you a better study map than a long list of pediatric diseases. It organizes the exam by physician task and organ system, so you can see both what decisions are tested and which areas receive more emphasis. Start with the NBOME COMAT Clinical Pediatrics outline, then build your study plan around its current categories.
History and physical examination, including diagnosis, carries 30-35% of the blueprint. Diagnostic technologies account for 20-30%, and management for 20-25%. Respiratory topics and circulatory or hematologic topics each represent 11-14%, while several other systems fall in the 9-14% range. The task weights and system weights answer different questions: one shows what you must do, the other helps you choose the clinical material on which to practise.
| Content area | Blueprint weight | Study priority |
|---|---|---|
| History and physical examination, including diagnosis | 30-35% | Practise recognizing patterns in history and examination findings by age |
| Diagnostic technologies | 20-30% | Practise choosing the next test and interpreting results |
| Management | 20-25% | Practise first-line decisions and when to escalate |
| Respiratory system | 11-14% | Review age-specific respiratory findings and red flags |
| Circulatory and hematologic systems | 11-14% | Review age-specific cardiac and blood findings and red flags |
| Other organ systems | 9-14% | Cover each system with task-based practice, not disease lists |
| Social barriers, abuse recognition, anticipatory guidance, family communication | Named learner objectives; confirm current weighting in the outline | Make concise notes and practise questions for each |
The largest task category is recognition and diagnosis, followed by testing and management. That sequence gives you a useful practice loop: recognize a finding, decide whether testing is needed, interpret the result, then select management. A disease name matters because it supports those decisions, not as an isolated fact to memorize.
Why task categories beat disease lists
A disease list names topics but does not tell you which decision to practise. A task list does. Sort each question into five moves: recognize, test, interpret, manage, or disposition. This makes the reasoning visible, like tracing the steps in a clinical handoff rather than memorizing a shelf of diagnoses.
After a missed item, tag the move that broke down. If many errors involve selecting the next test, focus practice there. If misses are spread across the moves, review your approach across the full sequence. The pattern points to what needs attention without requiring you to treat every disease topic as equally urgent.
The objectives that disease lists crowd out
The blueprint also names social barriers to pediatric care, abuse recognition, anticipatory guidance and family communication. These objectives can disappear beneath long disease lists, even though they are part of what you are expected to learn. Give each a place in your notes and practise applying the ideas to questions.
General pediatric references help with clinical content, but they may not organize it around COMAT's task-based items. A topic-by-topic review can leave you unsure how to connect an age-specific finding to a test, result, management choice, or disposition. Use the pediatrics clinical reasoning guide as a related resource, while keeping the official outline as your guide to exam categories and weights.
Mapping exercise: Sort your notes into five columns: recognize, test, interpret, manage, and disposition. Then check which columns have few practice questions attached. A thin column signals a gap in task practice, even if your disease list looks complete.
Reading the Score and Pacing Your 120 Items
COMAT Clinical scores land on a scaled standard-score range of 9-200, and the number means little until you know the reference group. That group is first-time test takers from osteopathic medical schools who sat the assessment during 2023-2025, calibrated to a mean of 100 and a standard deviation of 10 (NBOME scoring and reporting). A score above 100 sits above that reference average.
It is not a universal pass mark. Each college of osteopathic medicine sets its own grading and performance policies, so a 100 from one school's scale and a 100 from another describe the same scaled position but not the same consequence.
The scale also absorbs minor difficulty differences between forms. That's the practical warning: a raw percentage from one practice set can't be compared with a raw percentage from another. Track scaled scores and item-level errors instead. For a percentile view of where a scaled score falls, the COMAT score percentile conversion reference does that arithmetic.
Pacing is trainable, and it's easier to train with a visible clock than with a vague sense of hurry.

At the 1.25-minute average, a timed block should put you at roughly 24 items by 30 minutes, 48 by 60 minutes, 72 by 90 minutes, 96 by 120 minutes and all 120 by the 150-minute limit.
| Elapsed time | Items reached (average pace) | Checkpoint use |
|---|---|---|
| 30 minutes | 24 items | Early check: are you ahead on straightforward items? |
| 60 minutes | 48 items | Halfway check: adjust if you are behind by more than a few items |
| 90 minutes | 72 items | Final-third check: decide how much time remains for long vignettes |
| 120 minutes | 96 items | Last-stretch check: reserve time for flagged items |
| 150 minutes | 120 items | Time limit: all items should be attempted |
Keep a pacing log during practice blocks: write down the item number you've reached at each checkpoint and compare it to the row. Two checkpoints behind is a signal to change how you read stems, not a reason to panic mid-block.
Flagged-item rule: answer, mark, move on. Return only if time remains after the final item. A flagged item you never revisit costs one point; a flagged item you nurse for four minutes costs several.
How to Work Through a Pediatric Vignette Step by Step
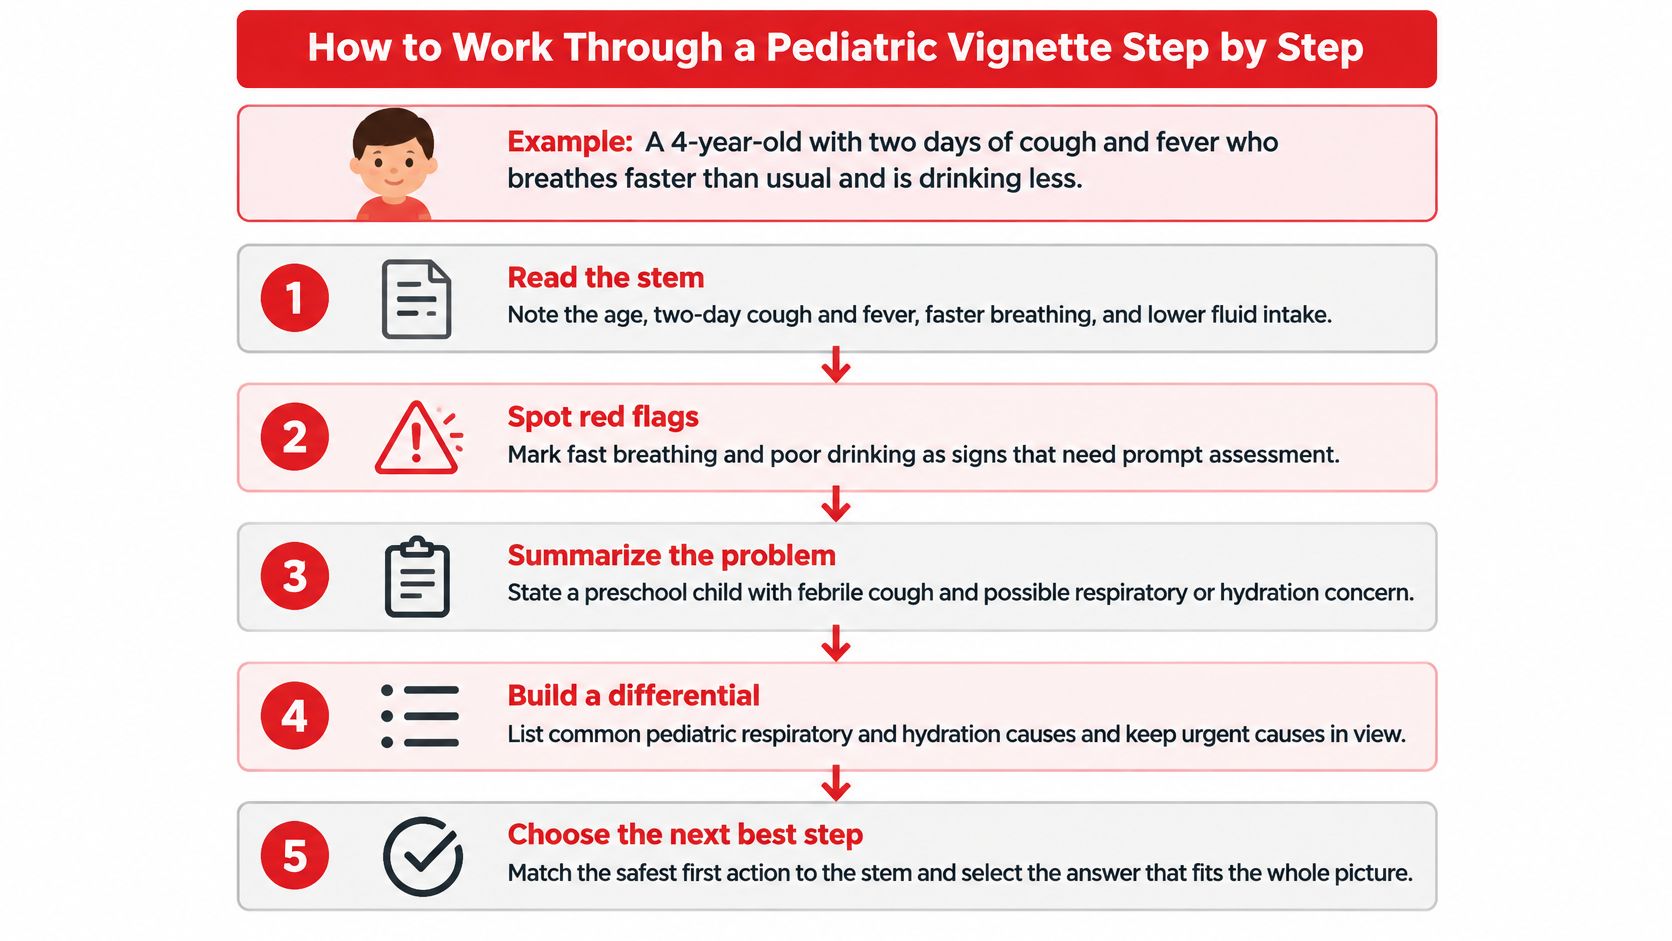
An original example makes the reasoning sequence concrete. A 4-year-old has had a cough and fever for two days, is breathing faster than usual, and is drinking less than half her normal amount. The question asks for the next step. Work through the clinical task, not a mental list of pediatric diseases.
- Set the age and developmental frame first. Normal respiratory rate, heart rate, blood pressure, hemoglobin, and developmental milestones vary with age. A value that may be reassuring in a school-age child can be concerning in a 2-month-old. Name the age band before comparing findings with answer choices.
- Name the presenting problem and check for red flags. In this example, fast breathing and poor intake deserve attention. Keep a mental checklist of respiratory distress, including retractions, grunting, or nasal flaring; dehydration; altered mental status; feeding changes; and events that may indicate a seizure.
- Identify the finding that changes the interpretation for this age. A sign can carry different weight at different stages of childhood. A febrile seizure in a toddler, a soft murmur in a newborn, and a bulging fontanelle each need to be interpreted in the relevant age context.
- Decide what the question asks you to do. Diagnosis, next test, and management are different tasks, so they can have different correct answers even when they use the same clinical details. Underline the ask before ranking the options.
- Reject choices that skip a safety step. If an option orders imaging before airway, breathing, circulation, and bedside glucose, it may be out of sequence. In a critically ill child, reversible physiologic threats come before definitive imaging or etiologic testing, as described in this pediatric coma management review.
- Choose a disposition and its threshold. Decide whether the child should be admitted, reassessed after a defined interval, or managed as an outpatient. Then name what would change that decision, such as an oxygen requirement, inability to keep fluids down, or an unreliable caregiving plan.
- Review why each option works or fails. Write one line explaining why the correct choice fits, then note what made each distractor tempting. Those near-misses can reveal whether you misread the ask, overlooked age, or chose the wrong clinical task.
A wrong answer you can explain is worth more than a right answer you can't.
This method also supports family communication, a task the blueprint names directly. Translate the clinical result into plain language a caregiver can use, much as a specialist may approach explaining IQ test results to parents. The subject differs, but the communication skill is similar: make technical information understandable without losing its meaning. Items on anticipatory guidance and counseling test that skill.
When an answer goes wrong, identify which step failed before choosing what to practice next. An age-specific vital-sign error calls for different review than a mistaken next-test choice or a rushed read of the final sentence. These test-taking strategies for clinical vignettes cover stem reading and answer elimination.
Use this sequence to reason through multiple-choice items, not to manage a real patient. Clinical decisions belong to supervising physicians using current guidelines.
A Study Timeline and Active Practice Routine
Eight weeks is a workable runway for a clerkship exam, and the plan below is a framework to shift against your actual test date. It isn't a school requirement and it doesn't promise a particular score. What it does is produce five artifacts you can inspect: a weak-area list, concept notes, a red-flag list, a pacing log and an error log.
| Phase | Weeks before exam | Focus | Output |
|---|---|---|---|
| Baseline | Week 1 | Timed mixed block logged by blueprint area | Weak-area list |
| Core content | Weeks 2-3 | History, examination and diagnostic content, weighted to the blueprint | Concept notes and practice items per area |
| Management and disposition | Weeks 4-5 | Management, escalation thresholds and disposition by age | Red-flag list by age group |
| Timed blocks | Weeks 6-7 | Full-length 2.5-hour blocks with pacing checkpoints | Pacing log and error log |
| Review and rest | Week 8 | Re-do missed items; reduce volume in the final days | Final error review |
The routine that runs inside every phase
Answer questions before you open a review chapter. Reading first feels productive and builds recognition, not recall. Commit to an answer, then read the explanation against your reasoning.
Keep one error log with three columns: what I knew, what I misread, and what I would do next time. The middle column is the one students skip and the one that pays. "I knew the diagnosis and still chose the wrong next test" tells you far more than a topic name.
Revisit missed items after two to three days rather than immediately. The delay shows whether the reasoning stuck or whether you only remembered the answer letter.
Honest limitation: this is a practice routine, not a validated method with a promised outcome. It converts study hours into artifacts you can audit, which is all a plan can honestly do.

For the rotation-level content review that feeds weeks 2 and 3, this walkthrough of how to study for the pediatrics shelf covers the topic blocks and their relative weight. Use it for content, then use the phases above for timing.
Set the date and time of your first timed block before you read further. A plan without a booked baseline is a list of intentions.
Choosing Practice Resources and Where Tutoring Fits
Four criteria decide whether a resource earns a place in your week: scope alignment with the current NBOME outline, currency of the content, question volume, and whether the explanations teach. Popularity doesn't appear on that list. Your error log should.
| Resource type | Best use | Main limitation |
|---|---|---|
| Official NBOME materials and current subject outline | Confirming scope, format and the blueprint | Limited practice volume; check current availability |
| Third-party question banks | High volume of practice items and explanations | Not official; check items against the blueprint and their currency |
| Pediatric textbooks and clinical guidelines | Deep review of concepts and age-specific thresholds | Not organized by exam task; time-consuming to search |
| One-on-one tutoring | Diagnosing reasoning gaps and reviewing the error log in detail | Complements official materials and independent study; does not replace them |
Start with the outline. It's short, free to consult, and it settles arguments about what to study. Then pick one question bank and finish it rather than sampling three. A bank you complete teaches you your own error patterns; three banks you half-finish teach you nothing comparable.
Textbooks earn their place when a concept won't stick, not as a default read-through. Guidelines help most for the age-specific thresholds that items love, such as when a febrile infant needs a different workup than a febrile preschooler.
Tutoring enters later, once the error log shows a repeating pattern. The useful question for a tutor isn't "explain pediatrics." It's "here are twelve misses, all in choosing the next test for infants, what am I misreading?" Ace Med Boards offers private tutoring for USMLE Step 1, Step 2 CK and Step 3, COMLEX-USA Level 1, Level 2-CE and Level 3, and selected Shelf and COMAT examinations. The ACE Progress Increase Guarantee does not apply to NBME shelf or COMAT shelf examinations, so treat shelf preparation as coaching on reasoning rather than a score promise.
Pediatrics-specific tutoring through pediatrics shelf exam tutoring works from that same question-analysis model. Skip any resource that claims access to recalled exam questions; it's both unreliable and a professional problem.
Confirm Your Exam Details and Choose Your Next Step
Exam day has a short checklist, and none of it is academic. Confirm your sitting date, time and delivery mode with your program office. Plan your arrival so a commute doesn't become the story. Budget for the tutorial outside your question time, and write your flagged-item rule on the scratch paper before item one.
- Checkpoint targets: set them from the pacing table, not from how you feel at item 40.
- Flagged items: mark and move. Return only after the last item.
- One clock habit: glance at elapsed time at each checkpoint rather than continuously.
Then look at your evidence. If practice blocks show the same reasoning error repeatedly, or the pacing log falls behind at two or more checkpoints, a one-on-one review session alongside your official materials and independent study is worth considering. Confirm current services on the Ace Med Boards website before inquiring, since availability for any given exam should be verified rather than assumed. Students also preparing for COMLEX-USA can read about that separate service on the COMLEX-USA tutoring page. Questions go to hello@acemedboards.com or through a scheduled appointment at the consultation link.
No single score defines a training path. Start the error log this week, and the next practice block will tell you more than any prediction could.
Sources
- NBOME, COMAT Clinical Subject Examinations, Pediatrics outline: blueprint weights and named learner objectives.
- NBOME, COMAT Exam Series: item count, 2.5-hour limit, 5-minute tutorial, psychometrically equivalent forms, and up to 10 administrations per subject exam per year.
- NBOME, COMAT Scoring and Reporting: 9-200 scaled score range, 2023-2025 first-time reference group, mean 100, standard deviation 10, and college-set performance policies.
- NBME, description of its pediatrics subject examination: context for distinguishing the shelf exam from COMAT.
- American Academy of Pediatrics, clinical guidance on age-specific vital signs and pediatric red flags, alongside peer-reviewed pediatric critical care references for vignette reasoning.
Byline: Ace Med Boards Editorial Team. Exam details remain time-sensitive.
If the pacing log shows you behind at two or more checkpoints, or the same reasoning error recurs, Ace Med Boards offers one-on-one tutoring for selected Shelf and COMAT examinations and COMLEX-USA preparation. Sessions can focus on question analysis and clinical reasoning. Visit Ace Med Boards to review current services and schedule a free consultation.




