

The MCAT total score spans 472 to 528, with a midpoint of 500, and each of the four sections spans 118 to 132, with a midpoint of 125. A “good” score is context-specific, so you should compare your total, section balance, current percentile, and target schools rather than chase one universal cutoff.
You may be looking at a score report and wondering whether a 501, 508, 514, or 520 changes your medical school options. The answer depends on more than the number printed beside “Total Score.” The fixed MCAT scale tells you where your performance falls on the exam's scoring system, while the current percentile table shows how that score compares with recent examinees. Your target schools, GPA, experiences, mission fit, and section profile complete the picture.
This guide focuses on MCAT and medical-school admissions preparation. It doesn't address USMLE, COMLEX-USA, Shelf exams, or residency applications.
What the MCAT Range Score Actually Is
The MCAT range score is the official scaled span available on the exam. Each of the four sections receives a score from 118 to 132, and the combined total ranges from 472 to 528, with 125 and 500 serving as the respective midpoints. The AAMC score-scale documentation explains that the total is calculated by adding the four section scores.
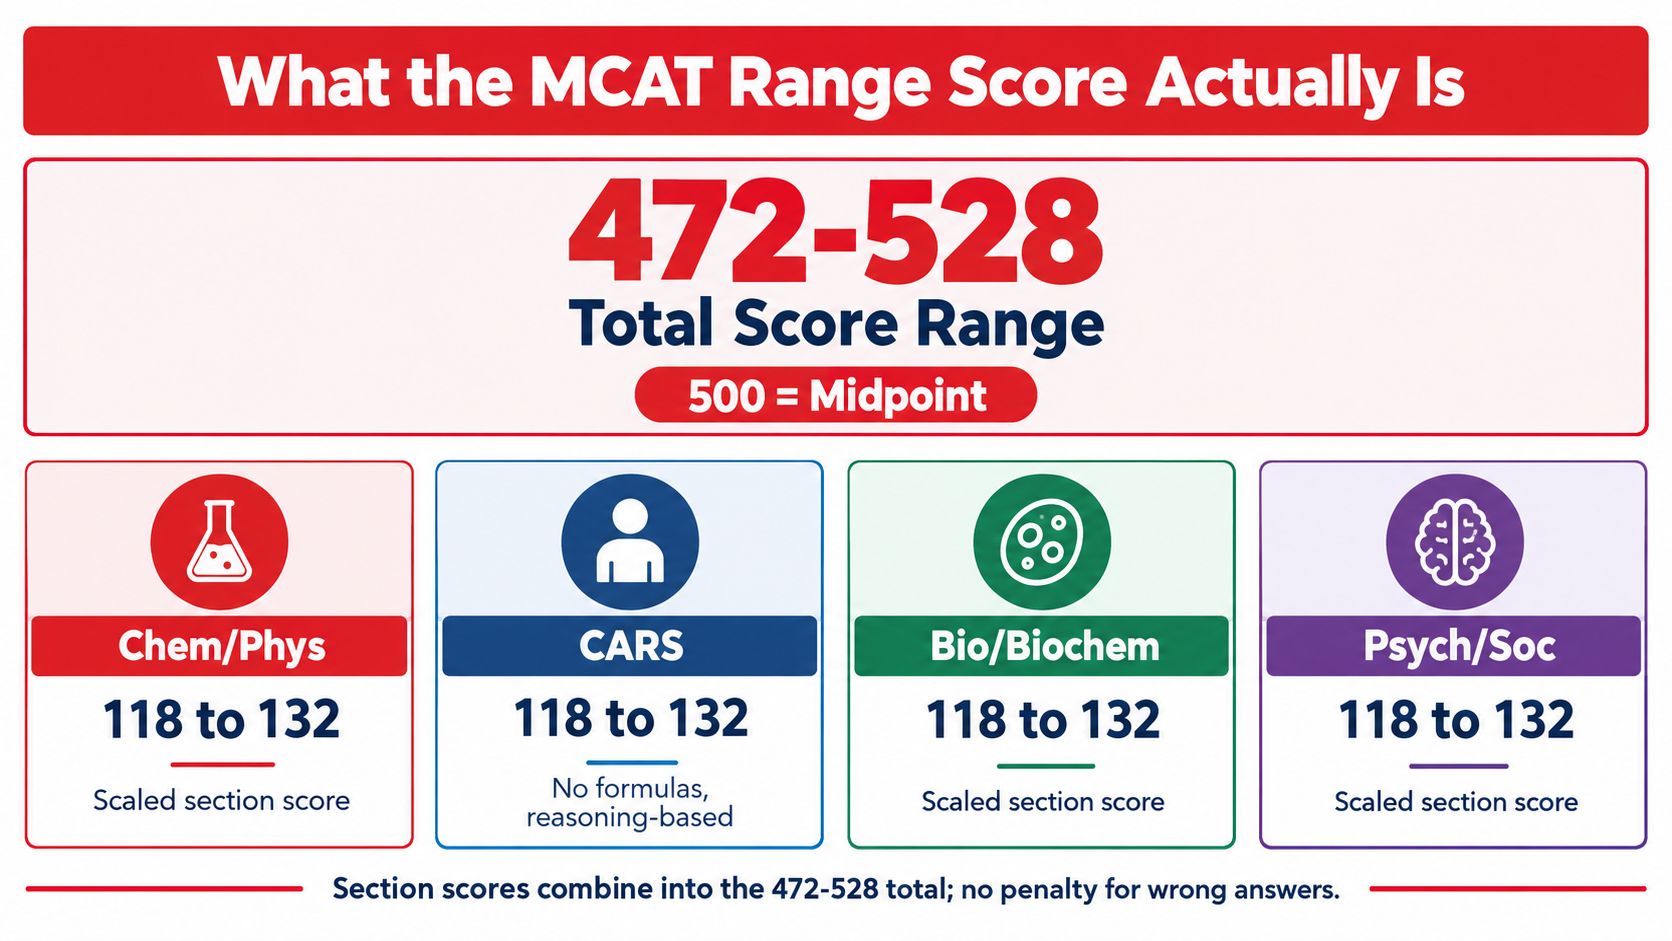
The four sections are Chemical and Physical Foundations of Biological Systems, Critical Analysis and Reasoning Skills, Biological and Biochemical Foundations of Living Systems, and Psychological, Social, and Biological Foundations of Behavior. A score report gives you a scaled result for each section and a total produced from those four results.
Scaled score versus percentage correct
Your MCAT score isn't a raw percentage. The number of questions you answer correctly is converted into a scaled score through an equating process. AAMC's official scoring explanation illustrates that different raw-score ranges can correspond to different scaled outcomes, such as a raw section result in the 35-37 range converting to 123, while a result in the 46-48 range might convert to 128.
That conversion helps account for differences in exam difficulty across administrations. You shouldn't compare the number correct from one test form with the number correct from another as if both forms were identical.
Practical rule: Use the scaled score on your official report for application decisions. Treat raw-question performance as a study diagnostic, not as an admissions metric.
The fixed scale and the moving percentile
The 472 to 528 scale remains fixed, but percentile ranks are updated using recent examinee data. A percentile tells you the percentage of scores equal to or below yours, so it adds comparative meaning that the scale alone can't provide. The same scaled score may have a somewhat different percentile in a later table.
For a concise explanation of the underlying score structure, see what the MCAT is scored out of. The useful question isn't, “Where is my score on the range?” It is, “Where is my score now, how balanced are my sections, and how does that profile compare with the schools on my list?”
Section Scores, Total Score, and Why Balance Matters
The total score is the sum of four equally contributing section scores. Those sections are commonly shortened to C/P, CARS, B/B, and P/S. Because the composite adds the four results, two applicants can reach the same total while presenting noticeably different academic profiles.
Consider this original comparison:
Two applicants, same total, different profiles
| Applicant | C/P | CARS | B/B | P/S | Total |
|---|---|---|---|---|---|
| Applicant A | 128 | 128 | 128 | 129 | 513 |
| Applicant B | 130 | 125 | 127 | 131 | 513 |
Applicant A's scores are tightly grouped. Applicant B demonstrates stronger performance in C/P and P/S, but the 125 CARS result creates a clear point of discussion. Neither profile can be labeled universally superior without knowing the schools, the applicant's academic record, and the program's educational priorities.
A committee may review the total first, then inspect the four sections for balance. A school with a strong emphasis on foundational science may pay close attention to C/P and B/B. Another program may value evidence of reading and reasoning across the application, making CARS a meaningful part of its review. Those are interpretive tendencies, not universal rules, and each institution sets its own process.
Why equal contribution doesn't mean equal interpretation
The arithmetic is straightforward, but admissions interpretation isn't. A one-point change in one section changes the total, yet it may also reveal a specific preparation issue. An uneven profile can result from content gaps, passage reasoning difficulty, timing, test anxiety, or an isolated testing-day problem.
You shouldn't respond by maximizing one section at the expense of the others. A very high section score can't erase every concern created by a substantially weaker section, just as a modest weakness doesn't automatically invalidate a strong overall application.
Admissions reading: The total answers “How did the composite turn out?” The section scores help answer “What kind of performance pattern produced it?”
Use your report to identify whether your profile is balanced enough for your target list. If one section stands apart, investigate the reason before deciding whether to retest or apply.
How Percentile Ranks Add Meaning to the Range
A percentile rank is a norm-referenced comparison. It represents the percentage of examinees whose scores were equal to or lower than yours. The scaled range is stable, but the AAMC updates percentile ranks annually using the most recent three years of testing data, as described in its MCAT scoring guidance.
The current AAMC table in effect from May 1, 2026, through April 30, 2027, uses combined testing-year results from 2023-2025. In that table, a total score of 508 corresponds to the 74th percentile, meaning 74% of scores were at or below 508. In the earlier 2021-2023 table, the same score corresponded to the 73rd percentile. You can verify the current figure in the AAMC percentile table.
A worked interpretation
Suppose an applicant sees a 508 on the score report. The score sits above the scale midpoint of 500, but the percentile supplies the more current comparison with peers. If the applicant later considers a score such as 515, the relevant percentile must be read from the table in effect for the application period, not copied from an older guide.
A higher scaled score within the same percentile table will correspond to a higher or equal percentile. However, the percentile attached to a particular score can shift as AAMC updates the comparison group. That's why a static statement such as “this score is always the 75th percentile” is unreliable.
Percentiles also help explain why a few points can matter near the middle of the distribution. Scores cluster around the central portion of the scale, so a modest increase may move an applicant past many other scores. That doesn't turn a score change into a guaranteed admissions result. It makes the current percentile a useful context marker.
The MCAT percentile explanation can help you read the distinction, but your application decisions should use the latest AAMC table and current school data.
Typical MCAT Ranges for MD and DO Programs
There isn't one verified national table that can responsibly assign fixed MCAT medians or 10th to 90th percentile ranges to broad labels such as “top-tier MD,” “mid-tier MD,” or “DO.” Program profiles differ, and a school's published data may describe its own applicant or matriculant population rather than a universal category.
A better approach is to treat program type as a starting point, then verify each school in the Medical School Admission Requirements database, or MSAR, and on the institution's current admissions pages. For osteopathic programs, consult current AACOMAS and school-specific information. The AAMC MCAT score-range guide is useful background, but it shouldn't replace primary school data.
A decision table without invented cutoffs
| Program context | How to use your MCAT range score | What to verify |
|---|---|---|
| Highly selective research MD program | Treat a strong percentile and balanced sections as helpful, not sufficient | Current MSAR profile, median and spread, research expectations, mission |
| Established regional MD program | Compare your total and sections with the school's own reported data | Residency preference, GPA profile, service expectations, school range |
| Newer or community-focused MD program | Examine mission fit alongside score context | Community engagement, geographic priorities, curriculum, current profile |
| Osteopathic medical program | Use AACOMAS and school-specific data rather than assuming one DO range | Prerequisites, GPA context, clinical exposure, mission and score history |
A score such as 508 may be a reasonable fit for some schools and a reach for others. A 514 can strengthen a broader list, while a 520 may reduce the likelihood that the MCAT itself is the main academic concern. None of these observations creates an admission probability, and none means a school will disregard GPA, experiences, writing, recommendations, or mission fit.
Why the middle ranges overlap
Public medical schools may evaluate in-state applicants differently from out-of-state applicants. A mission centered on rural health, primary care, or underserved communities may read the same score in light of service alignment and regional commitment. A school's published range can also include applicants with very different academic and experiential profiles.
Don't build a list from a national label alone. Mark each school as a fit, reach, or concern only after reviewing its current MSAR information, public admissions materials, prerequisite requirements, and mission.
Building a Personal Score-Context Worksheet
A worksheet turns an emotionally loaded score report into a set of concrete decisions. Record the official total and all four sections, then add the current AAMC percentile and the score information for every target school. The worksheet should also hold the non-score factors that determine whether a list is balanced.
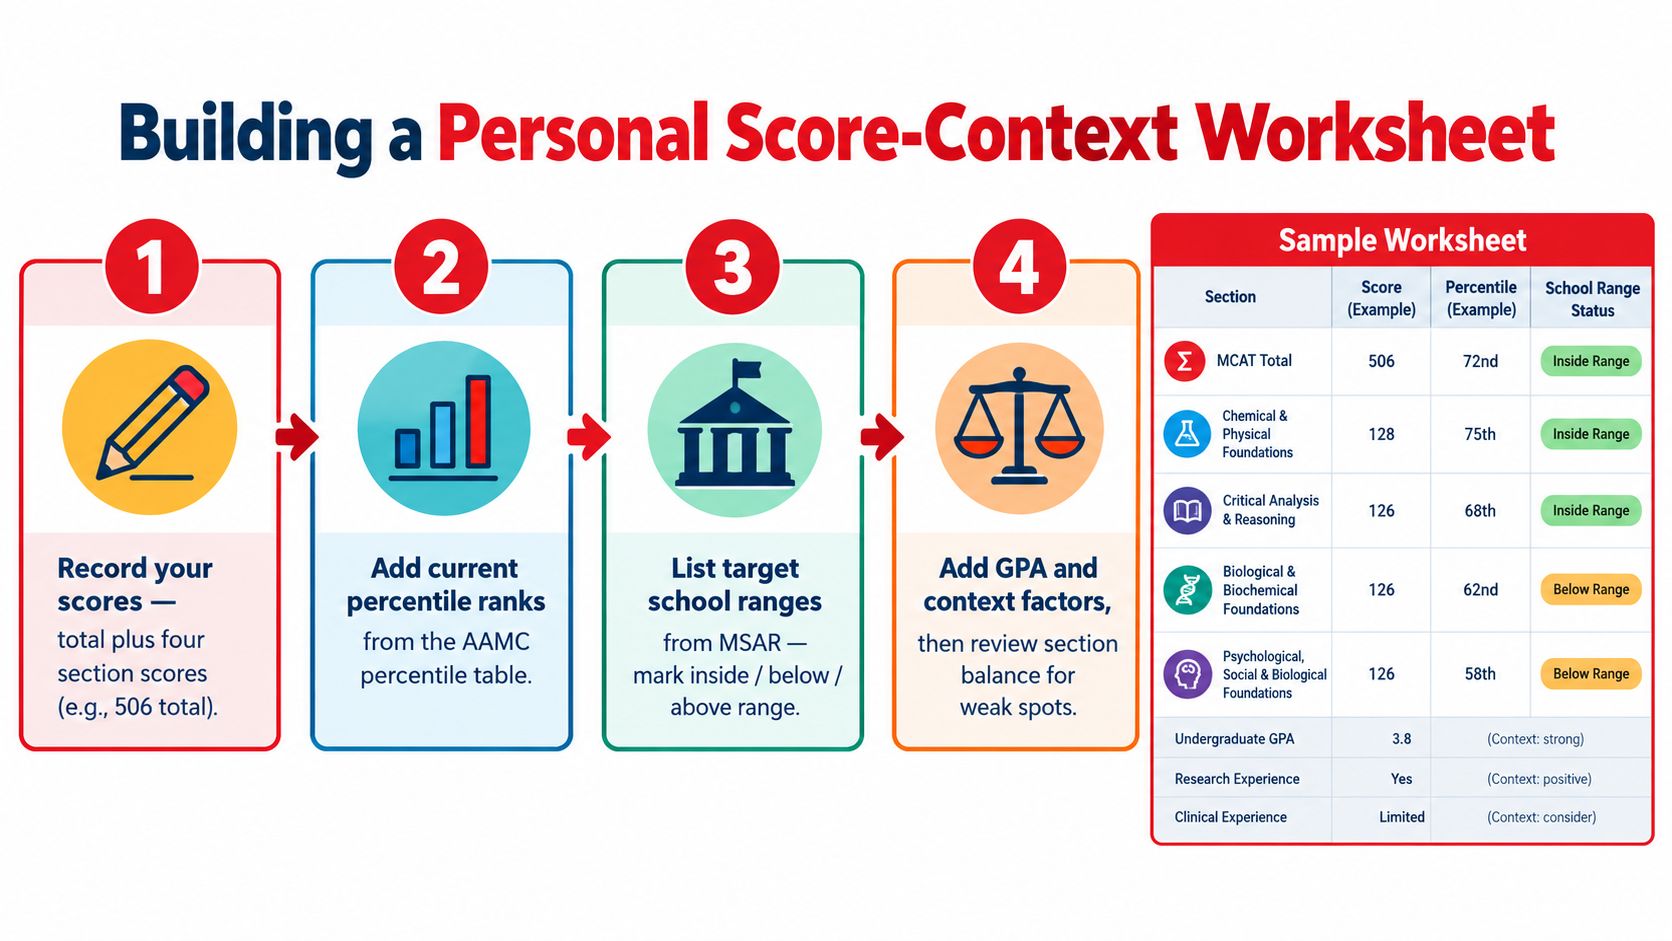
The worksheet fields
| Field | Your entry | Decision use |
|---|---|---|
| Total score | Official total | Compare with each school's current profile |
| C/P | Official section score | Identify science-strength or weakness |
| CARS | Official section score | Review reading and reasoning balance |
| B/B | Official section score | Review foundational biology and biochemistry performance |
| P/S | Official section score | Complete the four-section profile |
| Current percentile | AAMC table for the relevant period | Compare with recent examinees |
| Target-school range | Current MSAR or official school data | Mark inside, below, or above the reported range |
| GPA and context | Cumulative, science, trends, postbaccalaureate work | Interpret academic preparation as a whole |
| Retest factors | Practice trend, section diagnosis, timing, test history | Decide whether a retake has a sound basis |
For each school, add mission, location, public or private status, service priorities, and any relevant linkage or program notes. A score worksheet isn't a verdict. It exposes questions you can answer through deeper research.
Three hypothetical profiles
A balanced high scorer has a strong total with sections clustered closely together. That applicant can focus on school fit and the rest of the application rather than assuming every highly selective program is equally realistic.
A section-skewed mid scorer has a respectable composite but one section materially below the others. That profile calls for a closer review of target-school section expectations and a diagnosis of whether the weakness is stable or isolated.
A borderline retaker has a total below several target-school ranges, but practice exams show a clear, repeatable upward pattern and the applicant has enough time before the relevant deadline. Retesting may be reasonable, but only after confirming that preparation can address the diagnosed problem.
Use the worksheet as a shared document with a prehealth advisor. It supports a balanced list without turning a group range into an individual admission prediction.
Deciding Whether to Apply, Retake, or Adjust Your List
The question “Is my MCAT score good?” often hides three different decisions: Should I apply now? Should I retake? Should I change my school list? Separate those decisions before reacting to the score emotionally.
A three-path framework
Apply this cycle when your score and section profile sit reasonably within the current data for a balanced group of target schools, your GPA and experiences support the list, and your application timeline is workable. Being below a reported median doesn't automatically rule out an application, because a median isn't a minimum.
Retake only when you can identify a specific, addressable problem. Examples include a persistent section weakness, repeated practice-test evidence that differs meaningfully from the official result, or a preparation disruption that you can correct. A retake should have a reason, a study plan, and enough time before your application deadlines.
Widen or rebalance the list when your score is more competitive for a different group of programs than the one you initially selected. This isn't a retreat from medicine. It's a way to align school selection with current data, mission fit, geography, GPA, experiences, and your own priorities.
The low MCAT score guidance can help you consider options without treating a single result as a permanent judgment.
Edge cases deserve careful reading
A 500 with a 4.0 GPA may raise questions about standardized testing, but the answer depends on the complete academic record and the schools selected. A 520 with a weaker CARS section may still require section-level review, especially if the target schools emphasize broad academic readiness. A nontraditional applicant with a below-median total may bring a compelling academic trend, clinical record, or service mission that changes the context, without guaranteeing a favorable outcome.
Give yourself an evidence-gathering window before committing to a retake. During that period, review the official report, audit practice-test trends, inspect missed-question categories, compare current school data, and speak with a prehealth advisor. A decision based only on the total score is usually less reliable than one based on the full worksheet.
Study Planning Around a Specific Score Range
Start with your four section percentiles and rank them from weakest to strongest. Set a target band, not a promise of one exact number, then connect each study action to the type of problem your data reveals.
A profile-based study checklist
- Content gaps: Use the AAMC topic outlines to identify missing foundations, especially when a section result reflects incomplete knowledge rather than timing.
- Passage reasoning: For a section sitting in the 123-126 band, practice mapping the passage argument, identifying the question task, and eliminating choices with evidence from the text.
- Timing problems: Complete timed blocks and record where time disappears. Don't assume more content review will fix a pacing issue.
- Strong sections: Maintain competitive areas with shorter mixed sets so that concentrated work on a weak section doesn't create backsliding elsewhere.
- Question review: For every missed or guessed item, label the cause as a content gap, reasoning error, misread, calculation issue, or timing decision.
A question bank can provide repetition, while official AAMC materials help you understand the exam's intended style. Use both carefully and don't reproduce or seek recalled exam content. Your review process matters more than the raw number of questions completed.
A repeatable study rhythm
Schedule a full-length exam every two to three weeks, then reserve substantial time for review rather than treating the test as the end of the study cycle. Compare section trends, not just total scores. A total that rises while one section repeatedly falls may signal an emerging balance problem.
Revisit the plan every four weeks using updated practice data. One-on-one tutoring may be worth considering when a plateau persists, scores decline across several practice exams, or self-study hasn't resolved a section imbalance. Independent review and lower-cost resources may be sufficient when your errors are clear, your practice trend is stable, and you can execute the plan consistently.
For a structured starting point, review the MCAT study schedule framework. Any plan should remain flexible enough to account for coursework, employment, caregiving, health, and test anxiety.
Frequently Asked Questions About MCAT Score Ranges
How many times can I take the MCAT?
AAMC rules govern test attempts, voids, and score reporting. Because attempt limits and testing policies can change, check the current AAMC registration and testing information before scheduling. A voided exam may affect your testing record differently from a scored exam, so don't rely on informal advice when planning consecutive attempts.
When are MCAT scores released?
AAMC publishes a score-release date for each test administration. Check the current MCAT testing calendar for the applicable date and time, then confirm that the release fits your AMCAS submission plan. An official score report is the appropriate record for application use.
How long can schools use an MCAT score?
Schools set their own score-age policies, and AMCAS transmits MCAT history according to AAMC reporting procedures. Applicants with older scores, including nontraditional applicants and reapplicants, should review each school's current admissions page rather than assume one universal validity rule.
Who can access MSAR?
MSAR is AAMC's Medical School Admission Requirements database. Access, subscription terms, and any required fee are time-sensitive, so verify the current details on the official MSAR page. Free school websites can supplement MSAR, but they may not provide the same standardized comparison fields.
Do DO schools use the same application and score-history process?
Osteopathic applicants generally work through the separate AACOMAS application service and should review current AACOMAS and school-specific instructions. Don't assume every program interprets multiple MCAT attempts identically or sees only the latest result. Confirm how each school handles score history before deciding that a retake is harmless or necessary.
If you want help turning an MCAT score report into a practical school-list and retest decision, Ace Med Boards offers MCAT preparation and admissions consulting focused on score interpretation, study planning, and individualized next steps. You can visit the site to explore the available support and request a free consultation without treating tutoring as a guarantee of a particular score or admission outcome.




